Every protocol below comes from a clinical text or a website. Nothing here has a published trial behind it, so no two independent sources have been shown to agree. How often that happens
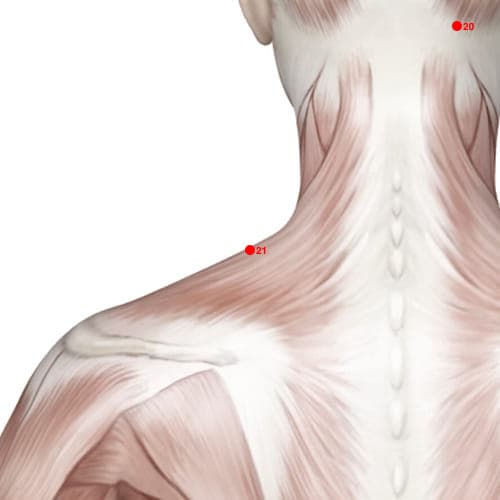
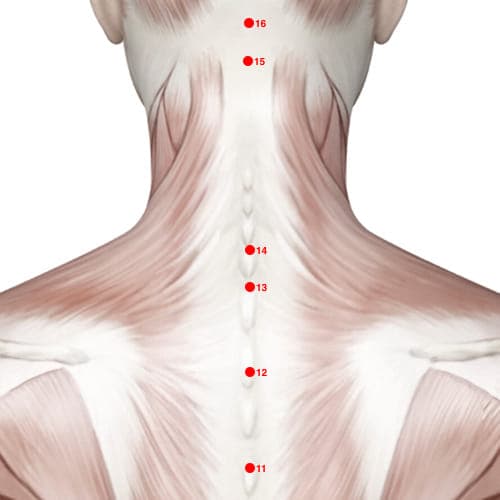
🎯 Location: On the shoulder directly above the nipple at the midpoint of the line connecting GV14 and acromion the at the highest point of the shoulder.
⚠️ Cautions: Avoid deep needling – risk of pneumothorax. Traditionally forbidden in pregnancy – these are the points used to bring on labour at term. Controlled data show no excess of preterm birth or stillbirth (Carr 2015), but in pregnancy needle only on a clear obstetric indication.
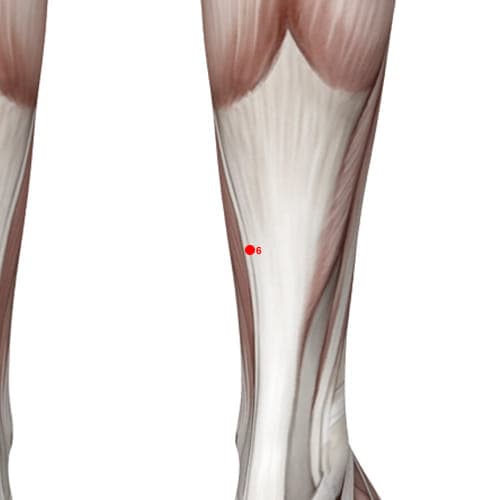
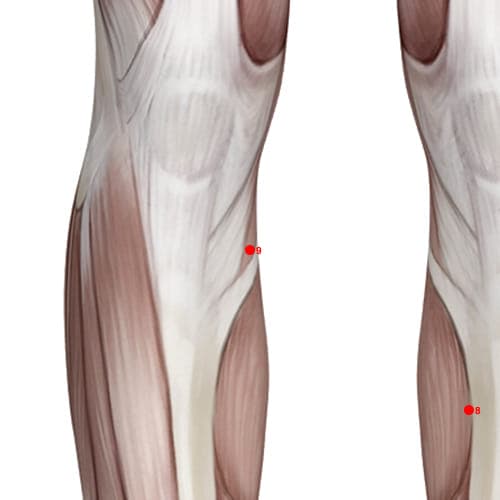
🎯 Location: 3 thumb widths directly above the tip of the medial malleolus posterior to the medial border of the tibia.
⚠️ Cautions: Traditionally forbidden in pregnancy – these are the points used to bring on labour at term. Controlled data show no excess of preterm birth or stillbirth (Carr 2015), but in pregnancy needle only on a clear obstetric indication.
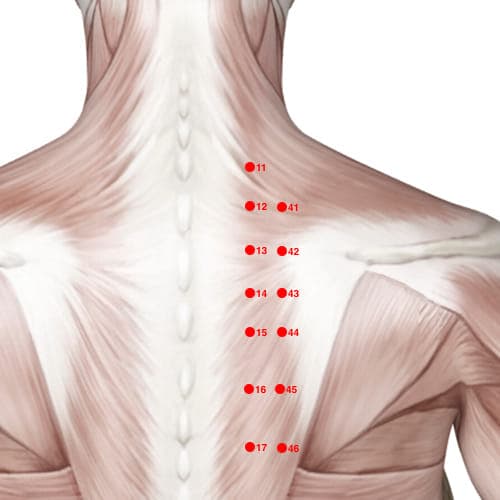
🎯 Location: 3 thumb widths lateral to the du mai at the level of the lower border of the spinous process of the 4th thoracic vertebra on the spinal border of the scapula.
⚠️ Cautions: Avoid deep perpendicular needling due to risk of pneumothorax.
🎯 Location: On the shoulder directly above the nipple at the midpoint of the line connecting GV14 and acromion the at the highest point of the shoulder.
⚠️ Cautions: Avoid deep needling – risk of pneumothorax. Traditionally forbidden in pregnancy – these are the points used to bring on labour at term. Controlled data show no excess of preterm birth or stillbirth (Carr 2015), but in pregnancy needle only on a clear obstetric indication.
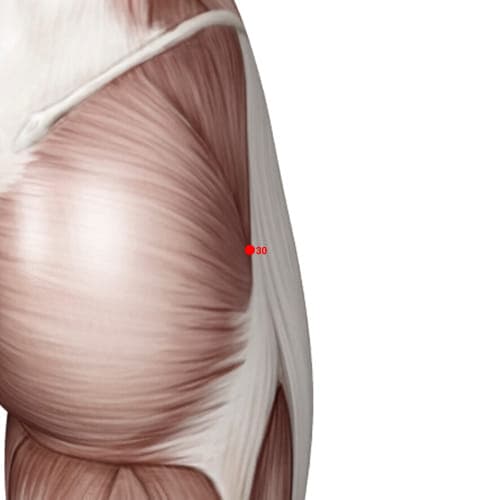
🎯 Location: At the junction of the lateral ⅓ and medial ⅔ of the distance between prominence of the greater trochanter and hiatus of the sacrum, GV02; when locating point put patient in the lateral recumbent position the with thigh flexed.